Personalized Medical Care & Dedicated International Patient Concierge

Medical Guide
Dental Crown in Korea: Materials, Process, and Longevity
A dental crown covers a weakened tooth to restore shape and chewing function. Published survival data give ranges, shaped by material, bite, and hygiene.
Schedule a ConsultationDental Crowns in Korea: What Materials Are Used and How Long Do They Last?
Medically reviewed by Dr. Park Hyo Jin, Specialist in Conservative Dentistry / Director
A dental crown is a custom-made cover that fits over a damaged or weakened tooth to restore its shape, strength, and ability to chew. If you are researching a dental crown in Korea, two questions matter most: which material will be used, and how long the result is likely to hold. The honest answer to the second is a range rather than a number — controlled studies report five-year survival for tooth-supported crowns in the mid-to-high 90s percent, while large real-world datasets report lower figures at ten and fifteen years. This guide covers the crown restoration process, what each material family does well, and the conservative reasoning that decides whether you need full coverage at all.
What a Dental Crown Is, and When One Is Genuinely Needed
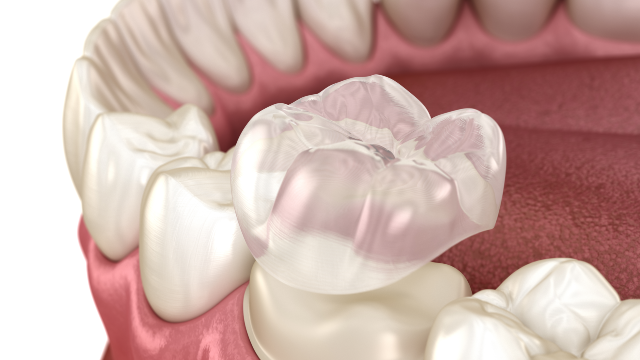
A crown is a single artificial tooth that fits over a real tooth which has been specially shaped to receive it. The American Dental Association describes it in those terms and notes that a crown can also fit over a dental implant. Magok Pureunmaeum Dental Clinic documents crown restoration as covering a damaged or weakened tooth with a custom-made dental crown to restore its shape and function.
The clinic's documented candidate profile is narrower than many patients expect: significantly damaged, weakened, extensively decayed, or fractured teeth that cannot be adequately restored with a simple filling. The trigger is not decay by itself — it is damage that has passed the point where a smaller restoration can do the job. Common situations where full coverage is considered include:
- A tooth that has broken, or one structurally weak enough to be at real risk of breaking.
- Decay that has removed so much tooth that a filling would have little sound structure to bond to.
- A tooth that has been root-canal treated and left with thin, unsupported walls.
- A cracked tooth where the crack has extended into the pulp, the soft tissue inside the tooth.
- A tooth anchoring a bridge, or an implant that needs its final restoration.
The evidence on cracked teeth is worth quoting carefully. The American Association of Endodontists reports research-based consensus that outcomes for endodontically treated cracked teeth are favorable when the crack is confined to the crown portion of the tooth and a full-coverage restoration is placed. It also states plainly that a crown on a cracked tooth provides maximum protection but does not guarantee success in every case — meaningful protection, no promise, which is the right frame for the whole topic.
Suitability depends on the remaining tooth structure, gum condition, presence of infection, and overall oral health — never on symptoms alone.
Why a Crown Should Be the Last Restorative Step, Not the First
Full coverage is the last step because preparing a tooth for a crown removes sound tooth structure that does not grow back. That single fact drives most of the professional caution around crowns.
The FDI World Dental Federation, the global federation of national dental associations, has endorsed Minimal Intervention Dentistry since 2002. Its position is that an operative, essentially surgical approach should only be used when specifically indicated — for example when a cavity cannot be arrested, or when there is a genuine functional or aesthetic requirement. The stated aim is to preserve dental structure and pulp vitality so that teeth stay functional for life.
The National Institute of Dental and Craniofacial Research, part of the US National Institutes of Health, adds the mechanical consequence. Fillings and crowns generally do not last a lifetime and may need replacing. Some natural tooth structure is removed each time a restoration is placed so it fits and functions properly. Repeating that cycle whittles the tooth down until too little structure remains to hold a restoration at all.
Large-scale outcome data point the same direction. A British Dental Journal analysis of roughly 1.2 million crowns placed in England and Wales found that when the data were re-analyzed for time to extraction of the restored tooth, crowns performed poorly — teeth restored with direct amalgam and resin composite restorations had better times to extraction.
This is the reasoning behind Magok Pureunmaeum Dental Clinic's stated philosophy: preserve natural teeth as much as possible while meeting patients' aesthetic needs, and perform only treatments that are truly necessary. Its documented clinic-wide approved claim is that extraction is considered only after preservation options have been thoroughly evaluated.
Crown, Inlay, or Onlay: A Short Decision Signpost
The choice between a crown, an onlay, and an inlay is decided by how much healthy tooth is left. The three sit on a spectrum of coverage:
- An inlay is a custom-made filling used when a regular direct filling is not ideal but a full crown is unnecessary. It is fabricated outside the tooth, then bonded or cemented into the prepared area.
- An onlay is custom-made to cover one or more damaged areas of a tooth — an option when a tooth needs more coverage than a filling but may still suit a more conservative restoration than a full crown.
- A crown covers the whole tooth and is documented for teeth that cannot be adequately restored with a simple filling.
The clinic notes that an onlay can restore tooth shape and function while preserving more natural tooth structure than a full-coverage crown in suitable cases. That is the core of the crown vs inlay onlay question, and it is a clinical judgment made after examination — not a preference you can settle in advance.
One caveat on the evidence: a Cochrane systematic review comparing single crowns with conventional fillings for restoring root-filled teeth found insufficient reliable evidence to say which is more effective for root-filled premolars that still have adequate crown structure.
Crown Materials: The Main Options and How They Behave
The crown materials dentistry uses today fall into three broad families — metal, metal-ceramic, and all-ceramic — with the all-ceramic family splitting again into layered and single-piece designs. A 2026 systematic review and meta-analysis pooled 64 clinical studies covering 3,509 metal-ceramic and 8,051 all-ceramic tooth-supported single crowns, and reported estimated five-year survival by material:
- Metal-ceramic (porcelain fused to metal). A cast metal substructure carries a layer of veneering porcelain for appearance. Reported five-year survival was 97.1%. It is the most heavily documented option — the British Dental Journal dataset alone included around 880,000 metal-ceramic crowns — and its weakness is chipping or fracture of the porcelain layer.
- Veneered zirconia. A densely sintered zirconia core layered with porcelain. Reported five-year survival was 97.3%, with the same layered-porcelain vulnerability.
- Monolithic zirconia. Milled from one solid piece of densely sintered zirconia, with no separate veneering layer. Reported five-year survival was 96.8%. The review found monolithic designs showed significantly fewer ceramic fractures and chipping events than veneered alternatives.
- Monolithic lithium-disilicate glass-ceramic. Also single-piece, in a glass-ceramic generally more translucent than zirconia. Reported five-year survival was 98.5%, the highest figure in the group.
- Full-metal crowns, including cast gold alloys. No ceramic layer to chip, which is mechanically favorable, but appearance restricts practical use to back teeth.
- Provisional (temporary) crowns. Usually resin-based, made to protect a prepared tooth for weeks — not a long-term restoration.
Three cautions belong with those numbers. They are category-level estimates pooled across studies, describing materials rather than your specific tooth. Most represent five years of observation, a short window for something you hope to keep for decades. And the material used in your case is a clinical decision made at consultation: this clinic's published information does not specify which crown materials or laboratory systems it stocks, so ask directly, and treat any regulatory-clearance claim about a specific product as something to verify at source.
How the Right Material Gets Chosen for Your Tooth
Material selection is a trade-off between strength, appearance, and how much tooth has to be removed to make room. The factors a dentist weighs include:
- Where the tooth sits. Molars absorb the heaviest chewing loads; front teeth are judged mainly on translucency and shade match.
- How much sound tooth remains. Materials need different minimum thicknesses, which changes how much preparation is required.
- Your bite and any grinding habit. The clinic lists habits such as teeth grinding among the factors affecting how long a restoration lasts.
- The opposing tooth, because the two surfaces wear against each other for years.
- Gum health. Active gum disease, significant oral infection, or inadequate oral hygiene may need addressing before definitive prosthetic treatment.
- Existing restorations and whitening plans. Whitening lightens natural enamel but not crowns, veneers, or fillings, so the clinic notes the sequence should be planned carefully when restorations are present.
- Your medical history, including medications, allergies, previous dental treatment, and any history of sensitivity.
Diagnosis here is supported by 3D CT imaging and a digital diagnostic system described as in clinic-wide use, including one publicly listed CBCT (Cone Beam CT) unit.
The Crown Restoration Process, Step by Step
The crown procedure steps documented by the clinic are compact: the tooth is evaluated and prepared, an impression or digital scan is taken, the crown is fabricated, and the completed crown is fitted and bonded. In practice that unfolds as follows:
- Examination and diagnosis. A dental examination is required to determine whether the tooth can be restored at all, and whether decay or infection needs treating first. Imaging is used when clinically indicated.
- Preliminary treatment where needed. Untreated infection, uncontrolled gum disease, or another active condition is addressed before a definitive restoration is placed.
- Anesthesia. Local anesthesia may be used when tooth preparation could cause discomfort; the clinic's documented position is that significant pain during the procedure is generally controlled this way.
- Tooth preparation. The tooth is reshaped to create space for the crown material and a margin it can seat against.
- Impression or digital scan. The prepared tooth and your bite are recorded, conventionally or with a digital scanner.
- Fabrication. The crown is made outside the mouth. Where a laboratory is involved, treatment normally spans more than one appointment and a temporary crown may be worn in the interval — a UK NHS restorative dentistry leaflet describes exactly this two-visit pattern.
- Fit, bonding, and bite adjustment. The finished crown is checked for fit, then fitted and bonded, and the bite is adjusted so the restored tooth meets its opposing teeth correctly.
- Review. The final result is assessed after the crown is permanently fitted and the surrounding tissues have settled.
If the tooth has had root canal treatment and is badly broken down, a post — a metal or fiber pin cemented into the root — is sometimes used to rebuild the core first. Whether that applies to you comes from the imaging, not a general rule.
How Long Crowns Last: What the Published Data Show
How long does a dental crown last? The defensible answer is a set of ranges from published data, plus the factors that move you within them. No dentist can promise a specific lifespan for an individual crown, and the clinic's own documentation is careful on this: longevity varies with oral hygiene, bite forces, crown material, and the condition of the tooth and gums.
What the published record shows, in ascending order of observation length:
- Controlled clinical studies at five years. The 2026 meta-analysis described above reported five-year survival between 96.8% and 98.5% depending on material, with metal-ceramic at 97.1%.
- Routine practice at five, ten, and fifteen years. The British Dental Journal analysis of about 1.2 million crowns in England and Wales reported 77% surviving to five years, 63% to ten years, and 53% at fifteen years. Patient age and level of treatment need influenced survival.
- Typical patient guidance. A UK NHS restorative dentistry information leaflet states that a properly cared-for crown or veneer should normally last around eight to ten years.
The gap between the controlled-study figures and the real-world dataset is not a contradiction: trials follow selected patients under close supervision, while population datasets capture varied hygiene, varied bite forces, already-compromised teeth, and many practitioners. The population figures are usually the more realistic guide over a decade.
For anyone planning crown recovery abroad, the clinic documents little downtime, with most patients resuming normal daily activities immediately, though temporary sensitivity or mild gum discomfort may occur.
What Shortens a Crown's Life, and What You Can Control
Most crowns do not fail because the material was wrong; they fail at the interface between crown and tooth, or because of forces the tooth was never going to withstand. The clinic's documented risks for crown restoration are:
- Temporary or persistent sensitivity, and gum irritation or tenderness.
- Bite discomfort after placement.
- Fracture or loosening of the crown.
- Recurrent decay around the crown margin.
- Problems with the supporting tooth, or the need for additional dental treatment.
The failure pattern documented for restorations more broadly is instructive. NIDCR-funded research covering more than 700,000 tooth-colored fillings in the United States found that 16% failed within five years, most often because of new decay (53%) or because the tooth broke or fractured (23%). Those are filling data, but the two dominant mechanisms — decay at the margin and structural fracture — are the same ones that end a crown's service life.
That tells you where your own effort pays off:
- Brush twice daily with a fluoride toothpaste and clean between the teeth daily. The margin where crown meets tooth is still vulnerable to decay.
- Avoid excessive biting forces, and keep hard objects — ice, pens, packaging — away from the restored tooth.
- Report grinding or clenching, and use whatever protection your dentist recommends.
- Attend the recommended check-ups rather than waiting for symptoms; a failing margin is usually visible on examination long before it hurts.
- Speak up promptly if the bite feels off, sensitivity persists, or the crown moves at all.
Who Plans and Reviews Crown Work at Magok Pureunmaeum Dental Clinic
Prosthetic Restoration is one of the clinic's eight documented specialties, covering crowns, inlays, onlays, and other restorative prostheses. The dentist whose profiled specialty covers this work is Dr. Park Hyo Jin, the clinic's Director, whose documented credentials are:
- Licensed dentist in South Korea, and a board-recognized specialist in Conservative Dentistry — the discipline concerned with preserving natural teeth through restorative treatment.
- Master's Degree in Dentistry from Wonkwang University Graduate School.
- Completed internship and residency in Conservative Dentistry, documented at Wonkwang University Dental Hospital.
- Over 22 years of clinical experience.
- Full member of the Korean Academy of Conservative Dentistry, the Korean Academy of Endodontics, and the Korean Academy of Esthetic Dentistry.
- Documented core specializations including restorative dentistry, esthetic dentistry, root canal treatment, and TMJ disorders.
These are Korean specialist qualifications and Korean society memberships. Korean specialist registration is registration in Korea; it is not the same thing as United States board certification and should not be read as equivalent.
The clinic's strongest documented quality differentiator is specialist-led diagnosis and treatment planning by a conservative dentistry specialist trained in a university dental hospital. Detailed sterilization and infection-control protocols are not publicly verified, so ask about them directly. The clinic has operated since 2017 and does not provide orthodontics or dentures, so a plan requiring tooth movement will need coordination elsewhere. You can read the practice background on its about-us page and patient feedback on its reviews page.
Planning Crown Treatment From the United States
For a crown dentist Seoul search, the practical questions are location, visits, verification, and cost drivers.
The clinic is on the 3rd floor of Woosung SB Tower, 385 Gangseo-ro, Gangseo-gu, Seoul 07586, about 50 meters from Exit 2 of Balsan Station on Seoul Metro Line 5. It is open Monday and Wednesday through Friday from 9:30 to 18:30 KST, Tuesday from 9:30 to 20:30, and Saturday from 9:30 to 14:00 with no lunch break, and is closed Sundays and public holidays. US patients typically fly into Incheon (ICN) or Gimpo (GMP).
On scheduling, the clinic documents that the number of visits depends on the treatment plan and the crown fabrication process, and that patients should confirm travel timing with the treating dentist. No fixed day count is published, so get that in writing before booking flights.
The clinic is a Registered Medical Institution for Attracting Foreign Patients, certified by Korea's Ministry of Health and Welfare under the Medical Overseas Expansion and Foreign Patients Attraction Act. Read that for what it is: a government registration required to treat international patients, not a clinical quality accreditation. Registered institutions have been required to carry medical malpractice liability insurance since 2016, and the government-supported Medical Korea portal maintains searchable lists of them. On language, the clinic states there are no language limitations and that multilingual support is available for all patient services, while describing interpreter arrangements as determined after consultation.
No cost figure appears in this article, because published pricing for this clinic is not confirmed and any number quoted before a dentist has examined your tooth is a guess. The drivers worth asking about are:
- How many teeth need restoring, and what condition each one is in.
- Which material is proposed, and why that one for this tooth.
- Whether preliminary treatment is needed first — decay removal, gum treatment, or root canal therapy.
- Whether a post and core is required to rebuild the tooth.
- Whether laboratory fabrication and a temporary crown are involved, and how many appointments that means.
- What follow-up, remake, or warranty terms apply if a problem appears after you return home.
You can raise these through the clinic's consultation contact page before committing to travel.
The Bottom Line
- A dental crown covers a damaged or weakened tooth to restore shape and chewing function, and is indicated for teeth that a simple filling cannot adequately restore.
- Crown materials divide into metal, metal-ceramic, and all-ceramic families; a 2026 meta-analysis of 64 studies reported five-year survival between 96.8% and 98.5% by material, with monolithic designs showing fewer chipping and fracture events than veneered ones.
- Longevity is a range, never a promise: routine-practice data on about 1.2 million crowns reported 77% surviving to five years, 63% to ten, and 53% at fifteen.
- Because full coverage removes tooth structure that cannot regrow, an inlay, onlay, or direct restoration should be ruled out first — matching this clinic's documented philosophy of treating only what is truly necessary.
- Crown work at Magok Pureunmaeum Dental Clinic falls under its Prosthetic Restoration specialty and is planned by Dr. Park Hyo Jin, a Korean board-recognized Conservative Dentistry specialist with over 22 years of clinical experience.
Frequently Asked Questions
Does a crowned tooth still need flossing?
Yes, and arguably more attentively than before. Recurrent decay around the crown margin is a documented risk, and that margin sits exactly where brushing reaches least well. The clinic's aftercare guidance is regular brushing and flossing, avoiding excessive biting forces, and attending recommended check-ups.
Can a crown be placed on a tooth that has already had root canal treatment?
Often, yes — that is one of the standard reasons a crown is considered, because a root-treated tooth has lost internal structure and can be left with unsupported walls. Where it is badly broken down, a post cemented into the root is sometimes used to rebuild the core first. Whether that applies is decided from the examination and imaging.
Will the crown match the color of my other teeth?
Shade matching is part of material selection, and translucency differs between materials, which is why glass-ceramics are often discussed for visible teeth. What no material can do is change color later alongside your natural teeth — the clinic notes that whitening does not lighten crowns, veneers, or fillings, so plan the sequence before the crown is made.
Can I get a crown finished in one appointment?
The clinic has not published a fixed visit count; its documented position is that the number of visits depends on the treatment plan and the fabrication process. Where a restoration is made in a laboratory, more than one appointment is normally involved and a temporary crown may be worn in between. Ask for the schedule for your tooth before booking travel.
What happens if my crown loosens or fractures after I return home?
Loosening, fracture, and recurrent decay are all documented risks, so agree the process in advance. Ask before treatment what follow-up, repair, remake, or warranty terms apply once you are back in the United States. A dentist near you can assess an acute problem, but a remake usually needs records from whoever made the original crown.
Is a crown always better than saving the tooth with something smaller?
Not automatically, and the evidence is genuinely unsettled. A Cochrane systematic review found insufficient reliable evidence to say whether a conventional filling or full coronal coverage is more effective for root-filled premolars that retain adequate tooth structure. The FDI World Dental Federation's minimal-intervention position points the same way: operative intervention when specifically indicated, not by default.
This article is for general informational purposes and does not constitute individualized medical advice, and it is not a self-diagnosis tool. Treatment candidacy, technique, and expected outcomes can only be determined through a consultation with a qualified dentist.
More Articles
Continue reading our clinical guides.

Cavity Treatment Korea: Resin Filling vs Inlay or Crown
A resin restoration is usually enough when decay is small and the tooth's walls and cusps are intact. Larger damage points to an inlay, onlay, or crown.
Learn More

Inlay Onlay Dental Restoration vs Crown: How to Choose
An inlay or onlay restores a damaged tooth without full coverage. Published data show partial-coverage survival close to crowns, so choose by tooth left.
Learn More

Minish Dental Treatment: How It Preserves Tooth Structure
Minish dental treatment is a biomimetic restoration that rebuilds damaged teeth with precision-made blocks while removing as little enamel as possible.
Learn More